

Why in news?
A health explainer published by The Hindu on 1 October 2026 drew attention to Swyer syndrome and delayed diagnosis. This rare condition affects how reproductive organs develop before birth. A person has a 46,XY chromosome pattern, but the reproductive organs called gonads do not become functioning testes or ovaries. Female external anatomy and a uterus may therefore coexist with that chromosome pattern. The condition often becomes apparent when expected puberty changes or menstrual periods do not begin. Recognising the cause matters because care involves hormone deficiency, bone health, reproductive options and the risk of gonadal tumours. The article concerns an established condition, not a newly discovered disease or a new treatment.
Chromosomes, genes and organs have different roles
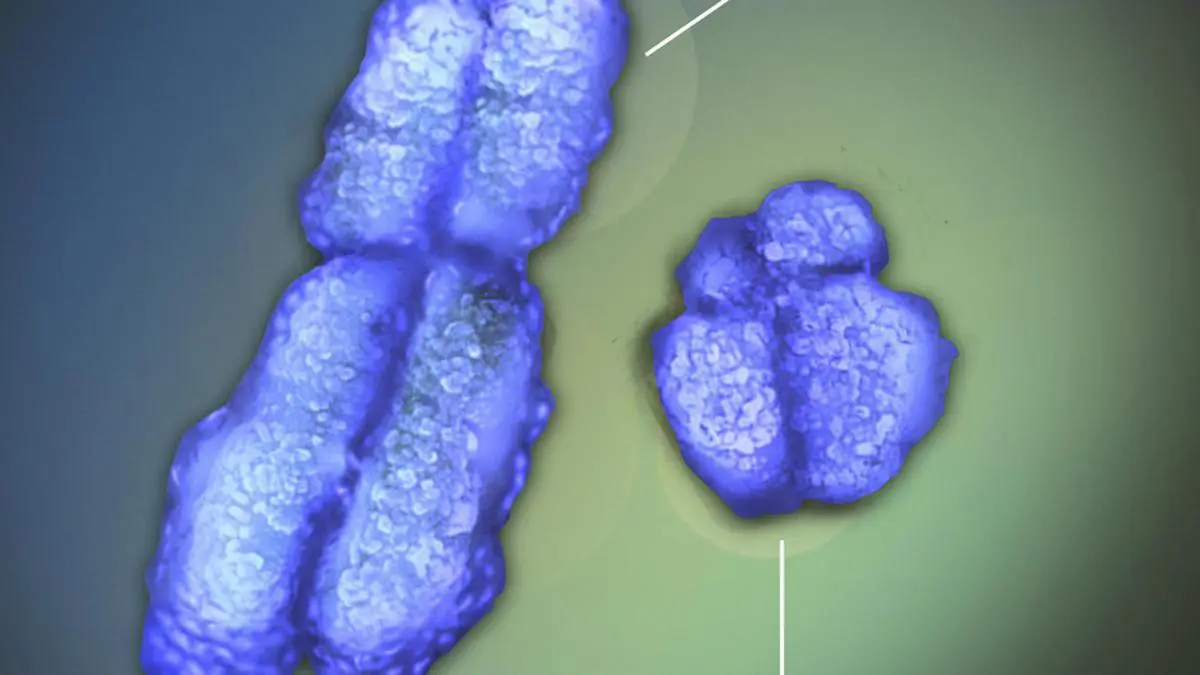
Most human cells contain 46 chromosomes, which carry genetic information. Two are commonly described as sex chromosomes, usually XX or XY. These patterns influence development through genes and the proteins they produce. They do not operate independently of those biological pathways. Understanding Swyer syndrome therefore requires a distinction between a chromosome pattern, the development of organs and the hormones those organs produce.
The medical name is 46,XY complete gonadal dysgenesis. Gonads are reproductive organs that normally develop as ovaries or testes; dysgenesis means their development has been disrupted. In Swyer syndrome, they are usually reduced to fibrous tissue called streak gonads. These do not provide normal reproductive cells or adequate sex-hormone production. The uterus and fallopian tubes can nevertheless develop, which has important implications for later care.
One relevant gene is SRY, named for the sex-determining region of the Y chromosome. It provides instructions for a protein that helps activate the pathway towards testis development. A change that prevents this protein from functioning can interrupt that pathway. MedlinePlus reports SRY variants in approximately 15% of people with Swyer syndrome. This is one mechanism, not an explanation for every case.
Other genes also participate in gonadal development, and the molecular explanation remains unidentified in some people. A condition can therefore be genetic without following a simple inheritance pattern in every family. Genetic counselling considers the findings in the individual rather than assuming that a parent necessarily passed on a known variant. A chromosome result describes one biological feature; it should not be used to infer someone's gender identity.
Why the condition may become apparent at puberty
External appearance at birth may not prompt investigation. Later, insufficient hormone production can mean that puberty does not progress as expected. A person may seek care because breast development is limited or menstruation has not started. The absence of a first menstrual period is called primary amenorrhoea. It has several possible causes, so that symptom alone does not establish Swyer syndrome.
Specialists bring together the clinical history, examination and laboratory findings. A karyotype is an analysis of chromosome number and structure. Hormone tests examine the signals involved in puberty, while imaging helps identify internal reproductive organs. Genetic tests may clarify the developmental pathway affected. These investigations answer different questions, which is why one appearance, symptom or test cannot replace the full assessment.
Treatment addresses several separate needs
Hormone treatment can support puberty changes and protect bone health when the body is not producing sufficient hormones. Where a uterus is present, the treatment plan also considers its lining. The choice and timing of treatment require specialist assessment. Replacing hormones does not change the chromosome pattern or make streak gonads produce eggs, but it can address important consequences of hormone deficiency.
Gonadal tissue requires a separate assessment because it can carry a significant tumour risk. Clinical guidance commonly recommends removal of the streak gonads following diagnosis, with counselling about the reasons and consequences. This is different from treating delayed puberty. A person may need both preventive management of the gonads and continuing hormone care, rather than one intervention solving every aspect of the condition.
Reproductive possibilities also depend on anatomy and individual health. Some people with a uterus can carry a pregnancy using a donated egg or embryo. In vitro fertilisation means fertilisation outside the body before an embryo is transferred to the uterus. This is a possible option, not a guaranteed outcome. Clear information, psychological support and respectful discussion help people consider these decisions without reducing their lives to a diagnosis.
Conclusion
Swyer syndrome illustrates why reproductive development must be understood through organs, genes and hormones together. Timely evaluation can explain delayed puberty and allow care to address health risks before they are overlooked. The practical goal is an individual plan covering development, long-term wellbeing and informed reproductive choices, with the person involved in decisions throughout.